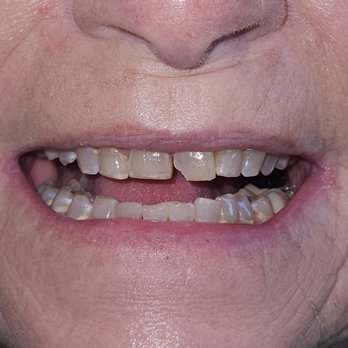
I usually don't check reviews or comment, but these are my opinions. I will state what my clear cut and straight forward policy is and always has been: that if there is a chance of saving a tooth, I often inform the patient, that "although I tried walking on water last week, I sunk all the way up to my knees." We can try our tooth saving process, but as in any field of medicine, there is no guarantee on the outcome. That becomes a patient's choice since I don't have a crystal ball. I ALWAYS tell the patient that it is their choice, and with their total knowledge and approval, I will proceed to try to save the tooth/teeth.
On almost a WEEKLY basis we see someone from out of the county who has heard about our Minimally Invasive practice and comes to see us asking if I can save their tooth that has been recommended for tooth canal treatment. The criteria for potential success is: has the tooth been sensitive to hot only?" which is almost always a symptom of a dead, nonvital, hopeless tooth. If not, then we can proceed with our ten-step treatment that we do on ALL compromised teeth to give them the best potential for survival, our routine service that very few dentists provide. I provide this knowledge in a lecture segment that I title: "The most unpopular lecture in dentistry, How to Keep Teeth Alive".
There is not the profit to be made in keeping teeth alive compared to doing root canals and crowns routinely or extractions or implants on any suspicious tooth, which is what the majority of dentists do to make money. At this point we have saved not only uncounted thousands of teeth (our success rate is off the chart) but have sacrificed MILLIONS of dollars in potential income, debunking the accusation that I am interested only in money. Any claim otherwise is a slanderous lie. Just ask my staff.
In response to my failures to summon up a crystal ball and predict in advance which teeth that have been neglected by the patient to the point of seeking help that will die despite our proven methods, I will point out that the implied recommendation to kill any suspicious tooth extrapolated out to stop any procedure with an unknown outcome means that we need to close the doors on MD Anderson Cancer Treatment centers since many of their patents die anyway. What an idiotic recommendation, but that IS the status quo in dentistry; kill any suspicious tooth.
How much of a status quo? Almost on a weekly basis we intervene in a treatment plan that includes unneeded root canals and crowns. Not once but TWICE we have intervened in our "Second Opinions", that we charge NOTHING for, on treatment plans that prescribed unneeded root canals and crowns on FIVE teeth that are protected by our lifetime, peer reviewed, published and advertized "Professional Lifetime Warranty on normal posterior teeth that erupt under our care". Look it up. There was ABSOLUTELY nothing wrong with these five teeth other than the dentist needed the money for whatever purpose. We provided a second opinion at no charge: find another dentist, and check with us on any prescribed treatment. It is unlikely that they will ever need any treatment involving decay on a chewing surface, and if there is, we will fix it for free.
Plus the caveat, since this "Professional Lifetime Warranty" is in the published, peer reviewed literature and used all over the world, by the legal rules of "Inform and Consent" the dentist MUST inform you of alternative treatments FOR YOUR CHILD that include Early Diagnosis/Early Intervention as outlined in the peer reviewed literature. Did your dentist do this? Did he/she just forge ahead with shots and drilling when 80% of ALL future dentistry can be prevented by ED/EI? If not, you have a legitimate claim of malpractice if not assault. We now have parents coming in for our "Second Opinion" because dentists are treatment planning for GENERAL ANESTHESIA to do sealants! ED/EI restorations that carry a professional lifetime warranty do not require anesthesia or shots and will stop at least 80% of all future dentistry for your child!!!!
Now for the idiotic suggestion to routinely prescribe prophylactic antibiotics. Starting with the caveat that prophylactic antibiotics are not recommended except in very clear situations, to prescribe a prophylactic antibiotic because a tooth MAY become non vital is not only malpractice, but will hide the fact that a tooth is non vital, and the infection will just crop up later on regardless, with the possible complication that the patient has now developed resistance to the antibiotic!! What an idiotic, uninformed recommendation.
Also, when making an accusation, a person must be truthful, admitting that giant cavities had been intentionally neglected, not that it was a cracked tooth, which is an entirely different set of circumstances and requires a totally different approach.
If you are interested in a straight forward treatment plan or a free "Second Opinion" contact us. read more